Joint pain alone does not identify the right operation. The useful clues are the joint involved, the tissue causing symptoms, examination findings, scan results, and whether the problem is repairable. By the end, you will know which procedures match common knee, shoulder, hip, ankle, elbow, and wrist problems, when non-operative care is the better choice, and what to ask during a surgical consultation.
Key takeaways
- Pain location alone cannot identify the damaged joint tissue.
- MRI and examination findings determine whether repair, trimming, or stabilisation is needed.
- Try therapy or injections first when symptoms lack a correctable structural cause.
- Ask about recovery milestones, surgical risks, and alternatives before consenting.
Which joint and tissue could be causing your symptoms?
Joint pain is not a diagnosis: the suspected tissue, not the location of pain alone, determines the arthroscopic procedure. Catching, clicking, true locking, giving-way, weakness, and instability each point toward different structures, and examination tests must confirm the pattern.
| Joint | Symptoms or examination clues | Possible arthroscopic target |
|---|---|---|
| Knee | Catching or locking | Meniscal tear or loose body |
| Knee | Giving-way or failed stability tests | ACL or PCL injury |
| Knee | Swelling, painful motion, or focal tenderness | Cartilage defect or synovitis |
| Shoulder | Overhead weakness | Rotator-cuff tear |
| Shoulder | Slipping, instability, or painful clicking | Labral tear or instability |
| Shoulder | Lateral pain or painful arc | Bursitis or impingement; assess biceps disease and loose tissue separately |
| Hip | Groin pain with flexion and rotation | Selected femoroacetabular impingement or acetabular labral tear |
| Ankle | Front-of-ankle pain, swelling, or catching | Anterior impingement, synovitis, osteochondral lesion, or loose body |
| Elbow | Stiffness, catching, or swelling | Loose body, synovitis, cartilage damage, or selected ligament problems |
| Wrist | Ulnar pain, clicking, or weakness | Triangular fibrocartilage-complex or scapholunate ligament injury, cartilage damage, ganglion-related condition, or loose body |
Hip, ankle, elbow, and wrist symptoms can arise from several small structures. Major ankle instability, deformity, or extensive arthritis may require open reconstruction rather than arthroscopy. A page about arthroscopy for joint problems worli should therefore help you identify the joint, tissue, and examination finding involved—not treat “joint pain” as the diagnosis.
How do scans and examination findings determine the exact operation?
The examination starts with injury timing, pain location, locking, instability, activity limits, previous treatment, and medical conditions. The clinician then checks range of motion, strength, alignment, stability, and joint-specific signs. A search for “arthroscopic surgery consultation worli” should lead to a plan based on these findings, not pain location alone.
Imaging supports that assessment. X-rays show fractures, alignment, joint-space loss, arthritis, and some bone spurs. MRI can show menisci, ligaments, labrum, rotator cuff, cartilage, and synovium. Ultrasound assesses superficial tendons, bursae, and dynamic shoulder problems. An abnormal scan does not prove it causes your pain; the history and examination must match.
The consultation should identify the exact structure and operation:
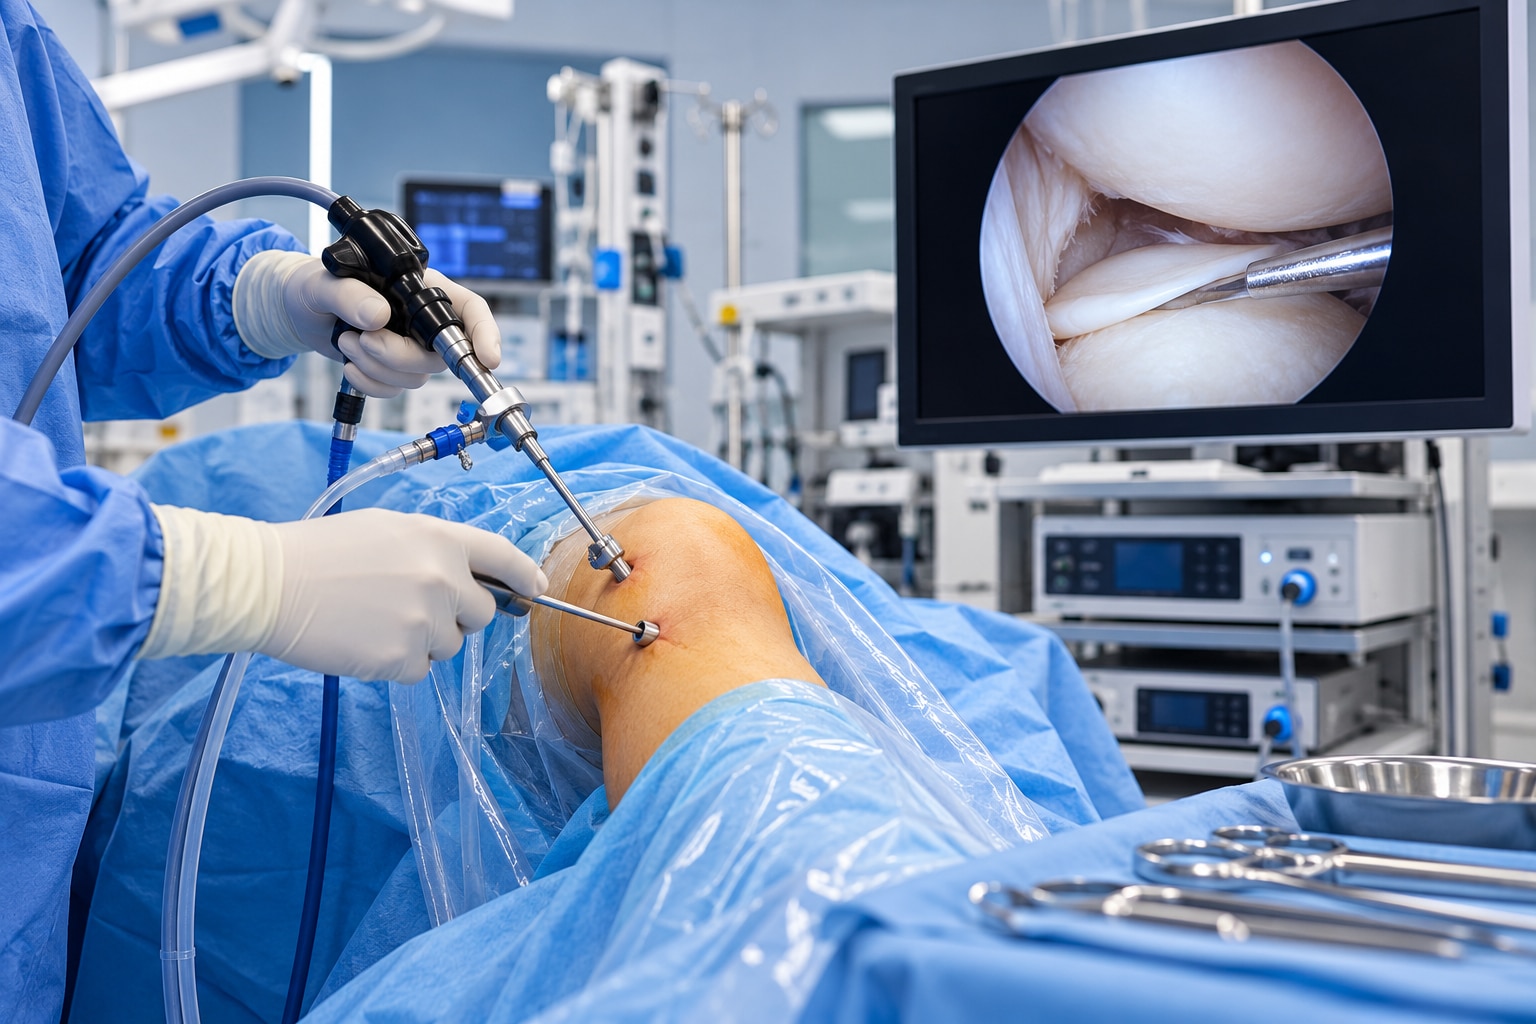
- Diagnostic arthroscopy directly inspects the joint when the diagnosis remains uncertain.
- Debridement removes damaged or inflamed tissue; meniscus trimming removes an irreparable fragment.
- Meniscus repair preserves and stitches suitable tissue, while ligament reconstruction replaces a damaged ligament with a graft.
- Cartilage procedures treat selected defects, not widespread arthritis.
- Shoulder options include rotator-cuff repair, labral or instability repair, biceps treatment, decompression, and distal-clavicle work.
Ask whether the proposed plan names the joint, structure, and exact procedure. “Knee arthroscopy” or “shoulder arthroscopy” alone is incomplete, because inspection, tissue removal, repair, reconstruction, and cartilage treatment have different aims and recoveries.
When is arthroscopy better than therapy, injections, or replacement?
Arthroscopy is better than continued non-operative care when a specific, repairable problem matches your symptoms and therapy, medication, injections, or activity changes have failed or are unsuitable. It is not automatically better for a scan abnormality.
| Option | Best fit | Main limitation |
|---|---|---|
| Physiotherapy and activity modification | Weakness, poor movement, stable degenerative symptoms | Does not remove a loose body or repair an unstable ligament |
| Medication or injection | Pain and inflammation control | Relief does not repair torn tissue or restore cartilage |
| Arthroscopy | Repairable traumatic tear, true locking from a loose body, documented ligament instability | Does not reverse osteoarthritis or worn cartilage |
| Open surgery | Major ankle instability, deformity, or reconstruction beyond arthroscopic access | Larger approach and different rehabilitation |
| Partial knee replacement | Severe arthritis confined to one compartment with suitable alignment | Not appropriate for widespread joint damage |
| Total joint replacement | Advanced, compartment-wide arthritis with persistent disabling pain | Replaces the joint rather than preserving repairable tissue |
Exercise-based rehabilitation can match arthroscopic partial meniscectomy for many middle-aged patients with a degenerative meniscal tear and knee osteoarthritis. A degenerative tear alone is therefore not a surgical indication. Knee lavage or debridement does not treat arthritis itself, and established hip osteoarthritis makes hip arthroscopy less predictable.
Arthroscopy is the wrong choice when infection, uncontrolled diabetes, another unsafe medical condition, major deformity, or ankle instability requiring open reconstruction has not been addressed. Surgery becomes reasonable only when the diagnosis, expected benefit, and alternatives align. A search for “arthroscopy options worli” should lead to that comparison, not a procedure chosen from pain alone.
What do recovery time and surgical risks depend on?
“Arthroscopy” does not predict recovery: the repaired structure determines how much protection healing needs. Removing a loose body or inspecting a knee may allow early weight-bearing, while repair preserves tissue but demands more patience than trimming or removing it.
| Procedure | Early restriction | Rehabilitation focus |
|---|---|---|
| Simple knee inspection or loose-body removal | Weight-bearing may begin early | Wound care, range of motion, gradual strengthening |
| Meniscus repair, ACL/PCL reconstruction, or cartilage procedure | Crutches and restricted loading | Protected motion, strengthening, return-to-sport testing |
| Rotator-cuff or instability repair | Sling and protected shoulder movement | Restoring range of motion before strengthening |
| Hip arthroscopy | Crutches with temporary movement or weight-bearing limits | Controlled mobility, hip strength, gait |
| Ankle, elbow, or wrist repair | Joint-specific limits to protect cartilage, tendon, or ligament | Structured motion and progressive loading |
Ask for milestones, not a generic recovery estimate: when you can drive, climb stairs, return to work, regain range of motion, start strengthening, and resume sport. A less invasive approach can still require substantial physiotherapy.
Recognised risks include infection, bleeding, blood clots, nerve or blood-vessel injury, stiffness, persistent symptoms, failed repair, and further surgery. Risk changes with the joint and operation, your age and medical conditions, smoking status, and postoperative mobility. Your surgeon should explain how each factor affects your plan.
What should you ask during an arthroscopy consultation in Worli?
A useful arthroscopic surgery consultation in Worli should identify the injured structure, prove that the examination and scans support it, and name the exact operation. Ask whether the plan is repair, reconstruction, trimming, removal, or diagnostic inspection—not simply “arthroscopy.”
| Option | What to clarify | Why it matters |
|---|---|---|
| Repair | Can the tissue be preserved and stitched? | Healing needs more protection than trimming |
| Reconstruction | Will a graft replace a damaged ligament? | Recovery and rehabilitation are longer |
| Trimming or removal | Which irreparable tissue or loose body will be removed? | Tissue removal does not correct every pain source |
| Diagnostic inspection | What question will inspection answer? | A normal finding may prevent unnecessary treatment |
Use this checklist when comparing arthroscopic procedure options in Worli or an arthroscopy options Worli search:
- What happens if the suspected lesion is absent or cannot be repaired? Can the plan change during surgery, and what consent covers that change?
- What are the alternatives: targeted physiotherapy, activity modification, medication, injection, or observation? Why does each option fit or not fit your diagnosis?
- Which joint and exact procedure does the surgeon routinely treat? Knee experience does not establish equivalent expertise in hip, shoulder, wrist, or ankle surgery.
- What are the weight-bearing, sling or brace, driving, work, and physiotherapy milestones?
- How will pain be controlled, and which warning signs require urgent review?
Choose an arthroscopic specialist in Worli for relevant joint-specific experience, not proximity alone. Shiva Orthopaedic Centre is one local setting to consider if the discussion covers diagnosis, alternatives, risks, and rehabilitation rather than pain alone.
Related services
Arthroscopic Surgery Arthroscopic Surgery in Worli – Dr. Kumar Dussa Dr. Kumar Dussa at Shiv Orthopaedic Centre, Worli, specializes in Arthroscopic Surgery, a minimally... View service → |
ACL Reconstruction Surgery ACL Reconstruction Surgery in Worli – Dr. Kumar Dussa Dr. Kumar Dussa at Shiv Orthopaedic Centre, Worli, specializes in ACL Reconstruction Surgery... View service → |
Frequently asked questions
Which joint and tissue could be causing my symptoms?
The suspected tissue depends on symptoms such as catching, true locking, giving-way, weakness, and instability. Examination findings help identify whether cartilage, a meniscus, ligament, tendon, or another structure is involved.
How do scans and examination findings determine the exact operation?
Your surgeon compares the physical examination with X-rays and, when needed, MRI findings. The combination can distinguish problems suited to repair, tissue removal or smoothing, ligament reconstruction, or another treatment.
When is arthroscopy better than therapy, injections, or joint replacement?
Arthroscopy is considered when a specific structural problem is causing symptoms and less invasive care has not resolved them. Therapy or injections may suit pain without a repairable lesion, while replacement is considered for advanced joint damage.
What does recovery time and surgical risk depend on?
Recovery depends on the joint treated, the procedure performed, whether tissue is repaired or removed, your baseline strength, and rehabilitation requirements. Risks include infection, bleeding, clots, stiffness, nerve or blood-vessel injury, and persistent symptoms.
What should I ask during an arthroscopy consultation in Worli?
Ask which tissue is causing your symptoms, what the scan shows, which alternatives exist, whether repair or removal is planned, how long weight-bearing restrictions last, and which warning signs require urgent care.
Keywords